

You’re sitting at a red light on the Tollway, and you notice your chin keeps drifting toward your left shoulder. You straighten it. A minute later, it drifts again. Your neck aches as you slept wrong, except you’ve “slept wrong” for three months now.
A lot of people in this spot try a new pillow, a massage, maybe a chiropractor. Some blame stress or too many hours on the laptop. Those guesses make sense, but when the head keeps pulling in the same direction on its own, the problem often isn’t in the neck. It’s in how the brain tells the neck muscles what to do.
That condition is cervical dystonia. So, what is cervical dystonia? It’s a neurological movement disorder in which neck muscles contract involuntarily, twisting or tilting the head into positions you didn’t choose. It’s the most common focal dystonia, meaning it affects one body region. It isn’t caused by bad posture, and it isn’t “all in your head” in the dismissive sense. With the right treatment, most people get real relief.
Medical disclaimer: This article is for general information only and doesn’t replace an exam by a doctor. Please don’t self-diagnose or start or stop any medication on your own; talk to a qualified provider about your symptoms.
What Dystonia Means
Dystonia is a group of movement disorders in which muscles contract when they shouldn’t, producing twisting movements, repetitive jerks, or stuck postures. The muscles themselves are healthy. The trouble sits in the brain circuits that coordinate them, including the basal ganglia and the cerebellum.
When dystonia mainly involves the neck, it’s called cervical dystonia. You may also see the older name, spasmodic torticollis: same condition, different label.
The head can move in several patterns, and many people have a mix:
- Turning, where the chin rotates toward one shoulder (the most common type)
- Tilting, where the ear drops toward the shoulder
- Pulling forward, with the chin toward the chest
- Pulling back, with the face tipping up toward the ceiling
- A sideways shift, where the head slides over the shoulders like a camera on a track
Some people also get a jerky or shaking head movement. Together with pain and stiffness, these make up the classic neck dystonia symptoms. Pain is a big part of it, too. Many patients come in for the ache long before anyone notices the head position.
The Early Signs That Get Missed
Cervical dystonia usually starts slowly, often between ages 30 and 50, and women get it more often than men. Early on, it can look like a stubborn muscle problem, which is exactly why it gets missed.
Common early signs of cervical dystonia include:
- An ache at the base of the skull or across the top of one shoulder that massage only helps for a day
- Your head drifting to one side while you watch TV or read, and someone else pointing it out
- A slight head tremor when you try to hold your head perfectly straight
- Neck control that gets worse when you’re tired, stressed, or in front of other people
- Trouble with tasks that need a steady head, such as backing out of a driveway or holding your gaze on a computer screen
Head tremor can also be confused with other conditions. Essential tremor, for example, can cause a “yes yes” or “no no” shake, and it’s a separate condition that our team also studies through its essential tremor research. Telling the two apart matters, because treatment differs.
Spotting these early signs of cervical dystonia sooner can save months of guessing.
Is It Dystonia or Arthritis?
Neck pain plus stiffness can come from a dozen places. Cervical spondylosis, the wear-and-tear arthritis of the neck, is extremely common after 40. A disc problem can cause pain that shoots into the arm, the kind of picture we discuss in our posts on cervical herniated disc issues.
What separates them is mostly movement. With arthritis, the neck is stiff and sore, especially after holding one position, but your head stays where you put it. With dystonia, the head moves on its own. You straighten it, and it pulls back again, sometimes with a tremor.
A few practical differences:
- Arthritis pain usually worsens with certain movements and eases with rest. Dystonic pulling often worsens with stress, walking, or concentration.
- A sensory trick (that light touch on the chin) doesn’t help arthritis.
- Arthritis rarely causes the neck muscles on one side to visibly bulge and work overtime.
Both can exist together. In fact, years of dystonic pulling can speed up wear in the neck joints. That’s why a neurologist looks at the whole picture, not only an X-ray. If involuntary movement is the main feature, cervical dystonia symptoms need a movement-focused exam, and imaging alone won’t answer the question.
Why It Happens and How It Is Diagnosed
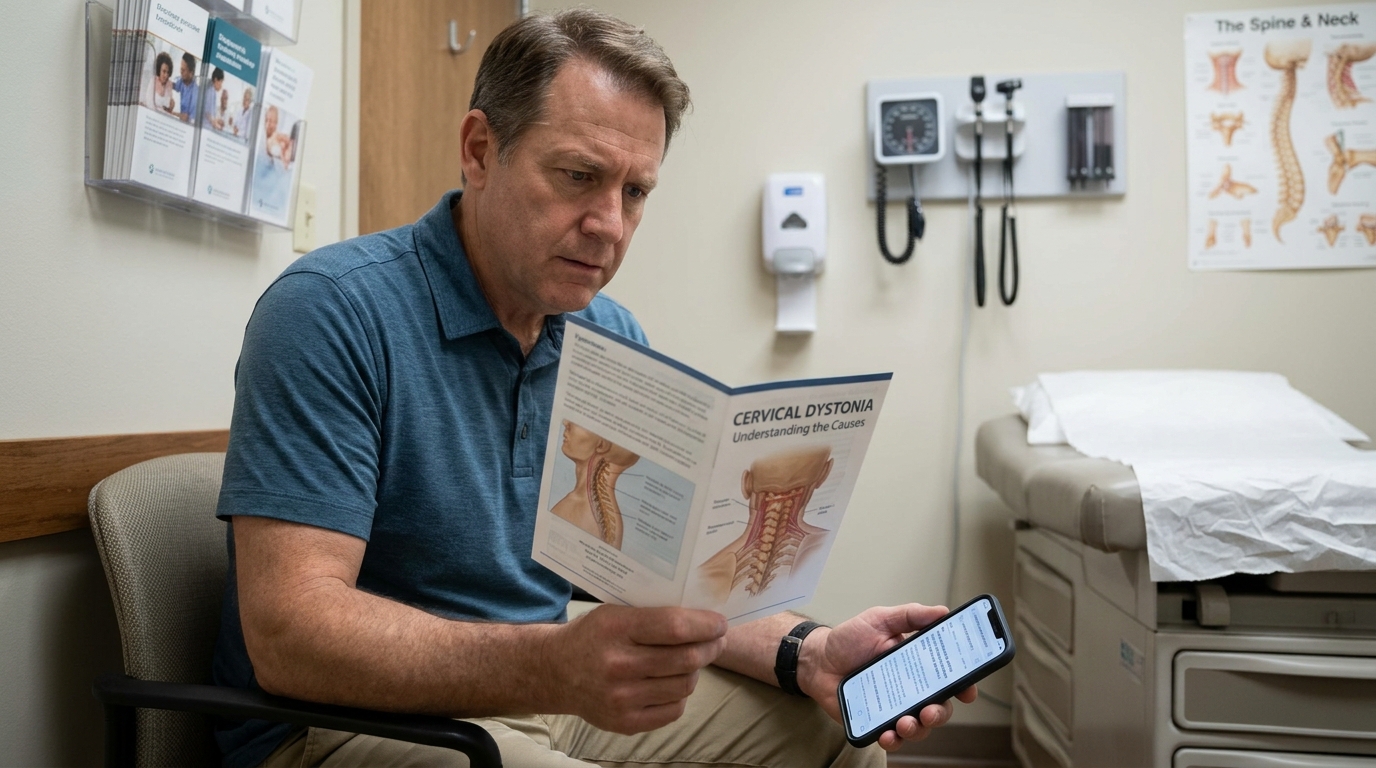
Most of the time, no one can point to a single cause. Most cases are idiopathic, meaning no clear trigger is found. Known cervical dystonia causes and risk factors include:
- Genetics, in a minority of people, especially when relatives also have dystonia
- Certain medications that block dopamine, such as some antipsychotics and anti-nausea drugs
- A previous head, neck, or shoulder injury, although timing alone doesn’t prove the injury caused it
- Being female and middle-aged, which raises the odds
So when you read about cervical dystonia causes online, keep in mind that most patients never get a single tidy explanation. That’s normal, and it doesn’t change how well treatment can work.
Diagnosis is clinical. No blood test diagnoses it. Your neurologist watches how your head sits at rest, while walking and during tasks, feels which muscles are overactive, and asks about medications and family history. We use MRI to rule out structural problems when something seems atypical, and our clinic offers MRI on Saturdays for patients who can’t get away on weekdays. EMG, which we do in the office, can sometimes help show which muscles are driving the pull.
Because this is a movement disorder, it’s worth seeing a neurologist who works with movement disorders regularly. Pinpointing the right muscles is half the battle, as the next section shows.
Botulinum Toxin: The Standard of Care
Botulinum toxin injections are the first-line cervical dystonia treatment. A review of placebo-controlled trials found that this treatment likely improves severity, disability, and pain compared with placebo.
Here’s how Botox for cervical dystonia typically works in practice:
- The toxin blocks the chemical signal between nerve and muscle, so the overactive muscles relax partially
- The doctor maps which muscles are pulling, since a head turned left can be driven by several different muscles
- Small injections go into those specific neck (and sometimes shoulder) muscles with a thin needle
- Relief often starts within one to two weeks
- The effect wears off over roughly three months, so injections are repeated, usually no more often than every 12 weeks
At Lone Star Neurology, we do Botox injections right in the office as one of our procedures. The first round is partly a fine-tuning visit. We often adjust doses and muscle choices at the second or third session based on how you respond.
Many people search for before and after cervical dystonia Botox photos to see what to expect. Those images can be encouraging, but they show one person’s best result. A realistic goal is less pulling, less pain, and easier daily tasks. A perfectly straight head every hour of every day isn’t typical. Results with Botox for cervical dystonia also vary from cycle to cycle, which is why follow-up matters.
Everything Else That Helps, and Where to Start
Injections work best as part of a bigger plan. Other pieces of cervical dystonia treatment include:
- Physical therapy, to keep the neck flexible, strengthen the opposing muscles, and reduce secondary stiffness
- Cervical dystonia exercises, usually gentle range of motion, posture retraining, and relaxation work, tailored to your pattern (aggressive stretching against the pull tends to backfire)
- Oral medications such as anticholinergics, muscle relaxants or benzodiazepines. They can help some people, but drowsiness, dry mouth, blurred vision, memory problems, and dependence risks limit them. A separate Cochrane comparison found botulinum toxin generally outperformed the anticholinergic trihexyphenidyl, which caused more side effects.
- Stress and sleep management. Stress doesn’t cause dystonia, but it clearly turns the volume up. Many patients notice the pull is worst on deadline days.
- Deep brain stimulation (DBS), considered by specialized surgical teams for severe cases that don’t respond to injections and medication
Support counts too. Some people avoid restaurants or video calls because they’re self-conscious about their head position. Talking about that openly with your care team, or with a counselor, is part of treatment, not an extra.
If you’ve noticed persistent cervical dystonia symptoms, the first step is an evaluation with a neurologist who can confirm the diagnosis and rule out look-alikes. Bring a short phone video of your head position on a bad day, a list of every medication you take, and notes on any sensory tricks you use. Those details help more than you’d think.
Dystonia symptoms rarely go away on their own, but they respond well to treatment that’s adjusted over time. Lone Star Neurology has 22 locations across Dallas-Fort Worth, Austin, Houston, and San Antonio, so ongoing injection visits can stay close to home. Persistent cervical dystonia symptoms deserve a real answer. To schedule a visit, call 214-619-1910.







Please, leave your review
Write a comment: